
Special to WorldTribune, September 15, 2026 Non-AI Real World News
 Commentary by R. Clinton Ohlers
Two groundbreaking studies have examined the federal Vaccine Adverse Event Reporting System data on vaccine injuries and the relationship to mRNA Covid vaccines and blood transfusions.
Nine Patients
The first paper, titled Potential Implications of COVID-19 Vaccination for Blood Donation: A Retrospective Case Series and Literature Review – Part I of II looks at nine patients and presents strong evidence that they were harmed by blood transfusions from the general supply contaminated with mRNA vaccine components and their chief product, the spike protein.
 The complications were not minor. They included progressive clotting disorders, thromboembolic disease, myocarditis, pericardial disease, disseminated intravascular coagulation, multi-organ system failure, and, in several tragic cases, death.
When these case reports were synthesized with the existing biomedical literature, a terrifying reality emerged that completely redefines the safety parameters of donor blood.
Every pathogenic component of the mRNA injections, including synthetic mRNA, DNA plasmids, SV40 promoters, and circulating spike proteins, has been shown to circulate in the blood of some vaccinated donors for months or even years after injection. The study’s findings demonstrate that blood donated by vaccinated individuals may contain these biologically active, toxic constituents, which can then be transferred to unsuspecting recipients.
A summary of the findings, with illustrations [see below] by co-author and McCullough Foundation fellow Nic Hulscher, first appeared on the “The Focal Points” Substack. The cases span ages, countries, and ethnicities.
Both studies passed peer review and have just been published in this month’s issue of the International Journal of Innovative Research in Medical Science.
What Comprehensive Audit of federal VAERS Data Revealed
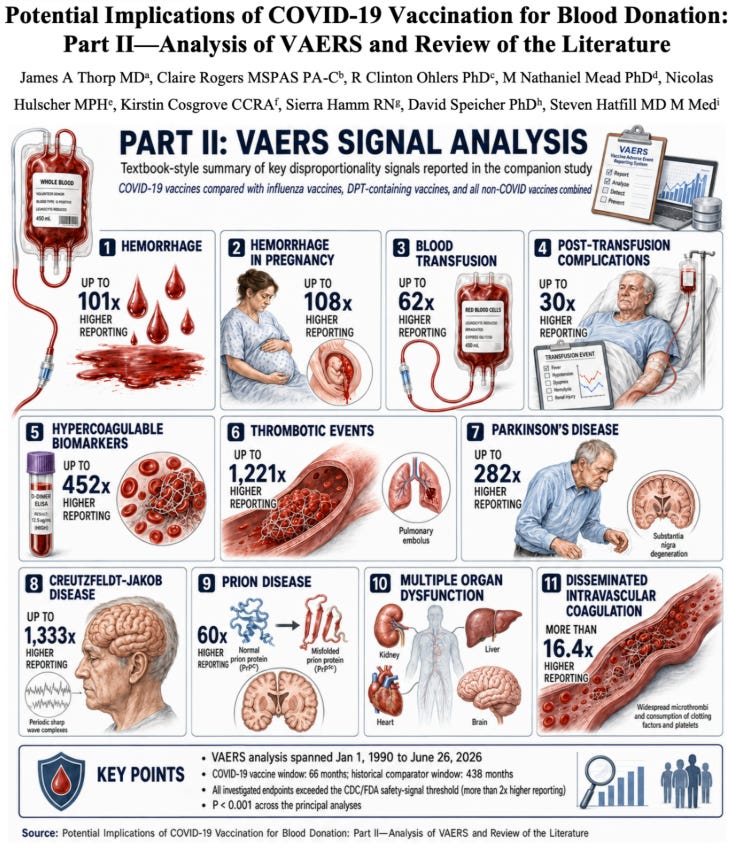
The second paper in our study, titled Potential Implications of COVID-19 Vaccination for Blood Donation: Part II: Analysis of VAERS and Review of the Literature, provides the massive, population-level statistical proof that validates our clinical findings. We executed a comprehensive pharmacovigilance audit of the federal Vaccine Adverse Event Reporting System database from January 1, 1990, through June 26, 2026, comparing reports associated with COVID-19 vaccines against those of influenza, DPT, and all other non-COVID vaccines combined.
The resulting safety signals linking the patient injuries in Part I to the the mRNA vaccines are stunning. As Dr. Michael Gaeta put it when I appeared recently on his show show Mondays with Michael (1:35:00), the extraordinary risk ratios (listed below) and P-value of 0.001 (representing the probability of causation between the mRNA vaccines and these categories of injuries about as close to certainty as is possible to be):
“This is not a 5-alarm fire. It is a 100-alarm fire,” he said.
The data represent a systemic, population-level disruption of the human vascular and neurological systems, reflecting the exact clotting and hemorrhagic pathologies documented in the Part I case series:
- Thrombotic events: up to a 1,221-fold increase
- Hypercoagulable biomarkers: up to a 452-fold increase
- Hemorrhage in pregnancy: up to a 108-fold increase
- Hemorrhage: up to a 101-fold increase
- Blood transfusion requirements: up to a 62-fold increase
- Post-transfusion complications: up to a 30-fold increase
- Creutzfeldt-Jakob disease: up to a 1,333-fold increase
- Parkinson’s disease: up to a 282-fold increase
- Prion disease: up to a 60-fold increase
Not only do blood related diseases dramatically increase after mRNA vaccination, but after transfusions as well.
Looking at pregnancy, in our earlier post SafeBlood: A Safety Net for Pregnant Mothers, Dr. Thorp and I noted that studies show that delivering mothers, during that window of time, are 10x to 13x more likely to require a transfusion than the general population.
Our analysis found that VAERS data indicates a risk for mothers who have had the mRNA vaccines as 108x (10,800%) that for mothers who received the influenza vaccines. This is risk on top of the already greater incidence of hemorrhage and transfusion during pregnancy.
All of these numbers provide devastating, undeniable evidence supporting what frontline observers have witnessed on the ground. By establishing these rates across a 36-year database, our study completely redefines how the discipline must evaluate the safety profile of the post-2020 donor pool.
As the studies’ medically credentialed [see below] co-authors point out, a study of nine cases is not capable of demonstrating proof. Rather, the scientific intent of these studies is to alert the public of the potential danger and to spur further a greater collection and analysis of data capable of establishing such proof, as well as to spur authorities to test the blood supply and protect patient rights to directed donations.
Here we have a pattern of injury across multiple patients, injuries not typical of blood transfusions before 2021, and these injuries have a cause. They did not appear spontaneously ex nihilo. There is no existing alternative theory, and that is a significant absence.
As Part II demonstrates, the most plausible — and I will say the only plausible — known cause are the mRNA genetic vaccines. If there were some other cause, somehow imitating the reported VAERS events in these nine particular cases, demonstrating such would require overwhelming evidence.
As I said in a recent co-interview with Steven Hatfill and Sierra Hamm on Dr. Joseph Sansone’s podcast, if cyanide were circulating in the water supply and then people in the vicinity immediately begin experience symptoms of cyanide poisoning, it would require extraordinary evidence to demonstrate that the water supply was not the source of the poisoning, and that the timing was just coincidence.
A further crime against humanity of the COVID era has been the authorities’ and willing media’s shifting the burden of proof.
Assuming a “safe and effective” narrative and dismissing every contrary report on the basis of this extreme bias has done irreparable harm to millions.
As in the early AIDS epidemic of the 1980s, if something is circulating in the blood, it stands to reason it can be transferred from one patient to another.
Medical authorities did the same with HIV in the 1980s as they are doing now, and a 1995 HHS internal review of that period admitted as much. We reference this review, HIV And The Blood Supply: An Analysis Of Crisis Decisionmaking, in Part I. The medical bureaucracies demanded absolute proof of harm while ignoring the common-sense rule of minimizing risk first.
Fearing an outbreak of hysteria about the blood supply, health authorities—which included a then young Dr. Fauci — sought to convince the public there was no proof of HIV transmission by transfusion. If such a risk did existed, it was “one in a million.” More likely, Fauci assured, that you would be killed by a mislabeled bag of blood than contract HIV (see, Marty Makary, MD, Blind Spots, 2024, Chapter 6).
Those claims defied common sense and reality. Thousands were infected unnecessarily, including roughly 60% of American hemophiliacs and the tennis great Arthur Ashe, who received tainted blood during hip surgery and later died — whether from AIDS or from the AZT used to treat it remains unknown. Public health authorities today, including statements on the FDA’s website, relying the American Association of Blood Banks (now renamed the Association for the Advancement of Blood and Biotherapies) and the American Red Cross, and America’s Blood Centers, have taken a similar or more aggressive stance, based on the false narrative that COVID-19 mRNA vaccines are “safe and effective.”
About 1.5% of the population receives a transfusion in a given year, and it appears a still smaller share are harmed by them. Nevertheless, the evidence is that the harm from mRNA vaccine components is real, and for some patients the evidence indicates it is profound and even life ending.
The sensible course is to avoid these risks. Gaslighting the public away from that protection is, in my view, another crime against humanity.
Illustrations:
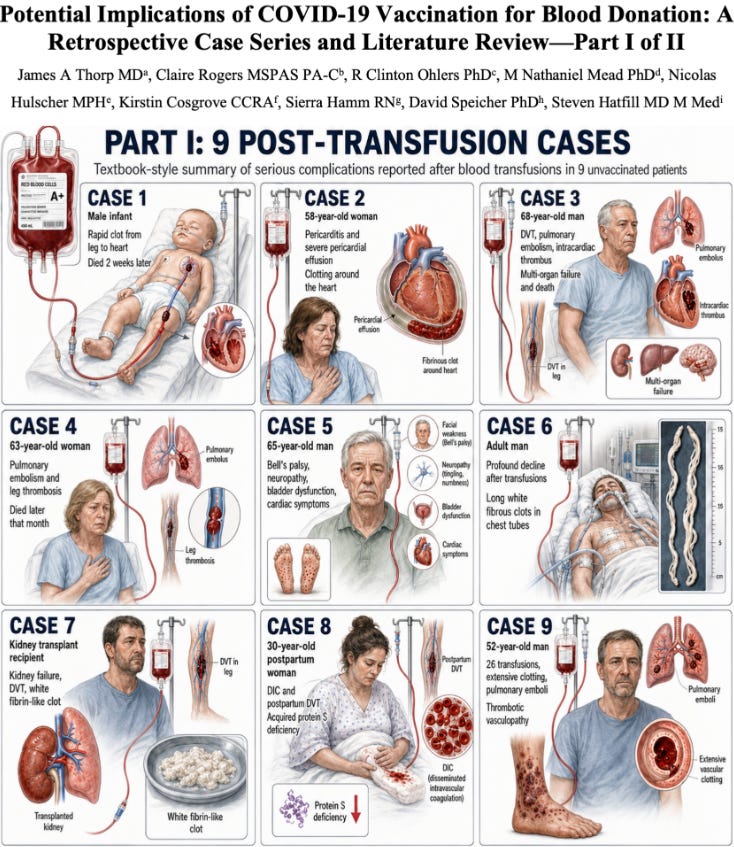
Illustrations courtesy of Nic Hulscher
About the authors: Dr. James Thorp, OB/GYN, MD, an outspoken advocate of Safe Blood’s work, is first author; I am third. In addition to editing and reviewing, my main contribution was providing eight of the nine cases the study examined. Another came from Dr. Pierre Kory. Del Bigtree and his producer Katherine at The HighWire, connected me with the family of another of these important cases.
Dr. Thorp assembled a powerhouse of co-authors to meet the highest scientific standards: Claire Rogers, our second author; Kirstin Cosgrove; Nick Hulscher; Sierra Hamm; Dr. David Speicher, whose work with Kevin McKernan brought to light DNA plasmid contamination in the mRNA vaccines; and, as senior author, the renowned Steven Hatfill.
R. Clinton Ohlers, PhD is former Investigative Editor at WorldTribune.com and currently Vice President of SafeBlood Donation. He was Research Assistant Professor in the Humanities at the University of Hong Kong at the time of the Covid outbreak in early 2020.
Support Free Press Foundation

New studies focused on mRNA vaccine injuries from transfusions added by Editor One on
View all posts by Editor One →